
Quick Answer
- Early Warning Signs: Non-healing wounds, redness, swelling or drainage from the foot
- Root Cause: Peripheral neuropathy and poor blood circulation impair healing
- Progression Risk: Ulcers can deepen, become infected and lead to tissue damage or gangrene
- Treatment Focus: Wound care with VAC/NPWT therapy, infection control, pressure offloading and blood sugar management
Synopsis
What Is a Diabetic Foot Ulcer?
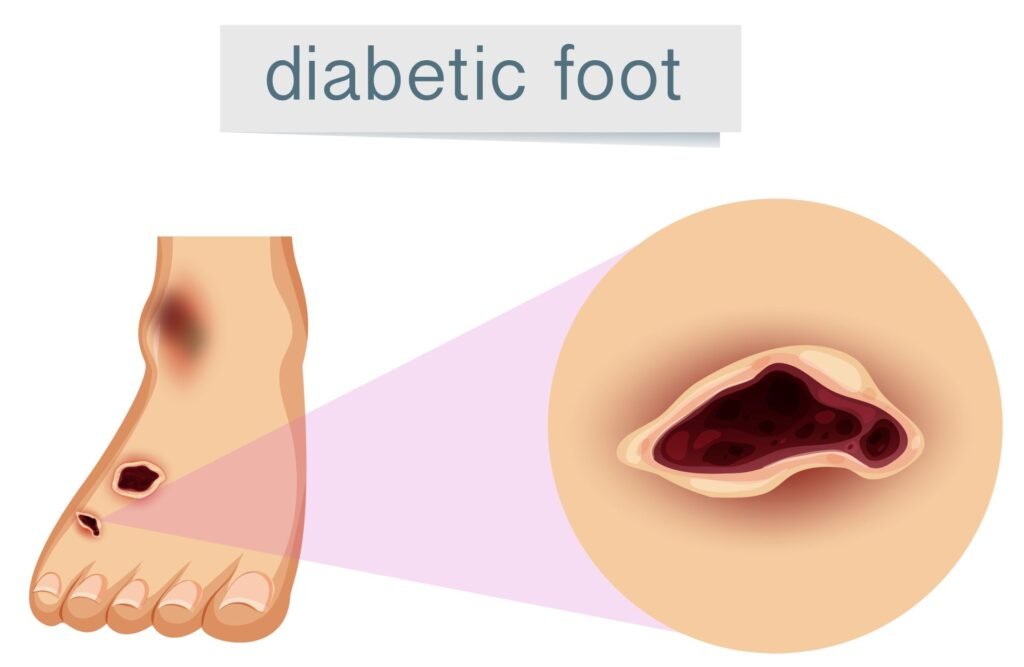
Causes of Diabetic Foot Ulcer
- Poor blood circulation (peripheral artery disease): Reduced blood flow limits oxygen supply to tissues, slowing healing and increasing the risk of infection.
- Peripheral neuropathy (nerve damage): Low blood supply leads to nerve damage. Neuropathy blocks pain, preventing patients from noticing cuts or wounds.
- High blood sugar levels (hyperglycaemia): Persistently elevated glucose impairs wound healing and weakens the body’s ability to fight infection.
- Pressure and foot deformities: Diabetic neuropathy can alter foot structure and walking pattern, leading to deformities like claw toes or hammer toes that create abnormal pressure points and increase ulcer risk.
- Minor unnoticed injuries: Small cuts, cracks, calluses or friction-related wounds can progress into ulcers due to delayed healing and infection risk.
Diabetic Foot Ulcer Symptoms
Early stage diabetic foot ulcer
- Persistent, non-healing wound on the foot or toes.
- Redness, swelling or warmth indicating inflammation.
- Drainage or discharge from the wound, which may stain socks or leak into your shoes.
- Pus or foul odour suggesting active infection.
Advanced stage diabetic foot ulcer
- Blackened or discoloured tissue due to tissue death.
- Numbness or tingling caused by peripheral neuropathy.
- Pain is absent despite severe tissue damage.
5 Stages of Diabetic Foot Ulcer
- Stage 0 (Pre-Ulcer / At-Risk Foot) Skin is intact with no open wound, but deformities, calluses or pressure points indicate a high risk of ulcer development.
- Stage 1 (Superficial Ulcer) Ulcers are limited to the outer layers of the skin without involvement of deeper tissues.
- Stage 2 (Deep Ulcer / Tendon or Ligament Involvement) Ulcer extends deeper into tissues such as tendons or ligaments, without bone infection.
- Stage 3 (Deep Ulcer with Infection / Osteomyelitis) A deeper ulcer associated with abscess formation or bone infection, indicating advanced disease.
- Stage 4 (Localised Gangrene – Forefoot) Tissue death (gangrene) affects a limited part of the foot, such as the toes or forefoot.
- Stage 5 (Extensive Gangrene – Whole Foot) Gangrene spreads across a large portion or the entire foot, often requiring surgical intervention.
When To See a Doctor for a Diabetic Foot Ulcer?
- Any foot wound that does not heal within 4-6 weeks or more.
- Loss of sensation, tingling or new numbness in the foot.
- Sudden increase in pain, swelling or change in foot shape.
- Signs of infection, such as redness, warmth or discharge.
- Foul odour or blackened skin (gangrene), indicating dead tissue or necrosis.
Role of Vascular Surgeon in Diabetic Foot Ulcers
Diabetic Foot Ulcer Treatment
- Wound debridement: Removal of dead or infected tissue to promote healing.
- Offloading: Use of specialised footwear, casts or braces to reduce pressure on the ulcer.
- Infection control: Antibiotic therapy based on severity and culture findings.
- Blood sugar management: Tight glycaemic control improves healing and reduces complications.
- Advanced wound care: Moisture-retentive dressings support tissue repair, while techniques like vacuum-assisted negative pressure wound therapy (NPWT) and pneumatic compression (Lympha Press) help manage wound drainage and support healing.
- Revascularisation: Procedures like peripheral angioplasty/bypass restore blood flow in severe cases.
- Surgical intervention: Required in severe cases for drainage, tissue removal or reconstruction.
Prevention of Diabetic Foot Ulcers
- Daily foot inspection helps detect early injuries or skin changes.
- Proper footwear reduces pressure points and friction-related damage.
- Regular cleaning and moisturising prevent cracks and skin breakdown.
- Maintaining controlled blood sugar levels supports healing.
- Avoid walking barefoot to reduce unnoticed injuries.
- Routine medical check-ups identify neuropathy and circulation issues early.
Take Home Message
FAQs
Can Diabetic Foot Ulcers Heal Completely?
Yes, early-stage diabetic foot ulcers can heal completely with timely wound care, pressure offloading and well-controlled blood sugar levels. Healing depends on adequate blood flow, absence of infection and consistent medical supervision However, advanced ulcers involving deeper tissues or infection may require specialised interventions such as debridement or vascular procedures. Regular follow-up and preventive foot care play an important role in reducing recurrence
How Long Does It Take for Diabetic Wounds To Heal?
Healing time depends on the stage of the ulcer, presence of infection and blood flow to the foot. Superficial diabetic foot ulcers may heal within 3 to 6 weeks with proper wound care and pressure offloading. Deeper ulcers involving tissue or infection often take 8 to 12 weeks or longer, especially if circulation is impaired. Delayed healing is common in patients with poor glycaemic control, neuropathy or vascular disease. Early treatment, infection control and consistent follow-up are key factors that determine recovery time.
What Are the Complications Associated With Diabetic Foot Ulcers?
Diabetic foot ulcers can worsen due to infection and poor circulation, leading to serious complications if left untreated.
- Deep tissue infection: Infection can spread beneath the skin into muscles, delaying healing.
- Osteomyelitis: Infection may reach the bone, increasing the risk of prolonged treatment.
- Tissue necrosis and gangrene: Poor blood supply can cause tissue death and blackened skin.
- Amputation risk: Severe infection or non-healing ulcers may require surgical removal.
- Systemic infection: Infection can spread to the bloodstream, causing life-threatening illness.
Yes, early-stage diabetic foot ulcers can heal completely with timely wound care, pressure offloading and well-controlled blood sugar levels. Healing depends on adequate blood flow, absence of infection and consistent medical supervision However, advanced ulcers involving deeper tissues or infection may require specialised interventions such as debridement or vascular procedures. Regular follow-up and preventive foot care play an important role in reducing recurrence. Healing time depends on the stage of the ulcer, presence of infection and blood flow to the foot. Superficial diabetic foot ulcers may heal within 3 to 6 weeks with proper wound care and pressure offloading. Deeper ulcers involving tissue or infection often take 8 to 12 weeks or longer, especially if circulation is impaired. Delayed healing is common in patients with poor glycaemic control, neuropathy or vascular disease. Early treatment, infection control and consistent follow-up are key factors that determine recovery time. Diabetic foot ulcers can worsen due to infection and poor circulation, leading to serious complications if left untreated.
- Deep tissue infection: Infection can spread beneath the skin into muscles, delaying healing.
- Osteomyelitis: Infection may reach the bone, increasing the risk of prolonged treatment.
- Tissue necrosis and gangrene: Poor blood supply can cause tissue death and blackened skin.
- Amputation risk: Severe infection or non-healing ulcers may require surgical removal.
- Systemic infection: Infection can spread to the bloodstream, causing life-threatening illness.